Confirmation
Download PDF
Open All
M06: Pediatrics - Cardiac Arrest
Updated:
Reviewed:
Introduction
Each year, BCEHS receives approximately 80 calls pertaining to cardiac or respiratory arrest for children between 0 and 12 years old.
To set expectations, it is important to understand that survival for out of hospital cardiac arrest (OHCA) rates remain low. They range from 6.6% for children under one, to 17.3% for children between 13 and 18.
Although the definition of pediatrics is up to and including age 17 years of age, the application of BCEHS Cardiac Arrest Guidelines applies as follows:
Ages Definitions and CPG Associated
|
|
Definition |
CPG |
|
Neonate |
Immediately after birth |
|
|
Pediatric |
Up to and including 11 years of age (or signs of puberty) |
M06: Pediatric Cardiac Arrest (current CPG) |
|
Adult |
Age 12 or older (or signs of puberty) |
Essentials
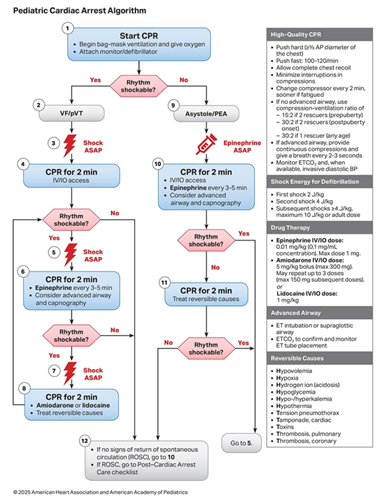
- High-quality cardiopulmonary resuscitation (CPR) is the foundation of pediatric cardiac arrest management. Chest compression to ventilation ratio 15:2 (two-rescuer) or 30:2 (single-rescuer) or continuous compressions with an advanced airway in place. Compress 1/3rd the depth of the chest at a rate of 100-120 per minute allowing full chest recoil. Minimize interruptions.
- Ventilate to visualize chest rise. Ventilation should be regularly reassessed and not use excessive tidal volumes. Use the monitor ventilation feedback if available to optimize ventilation.
- For initial non-shockable rhythms, administering epinephrine as soon as possible. Early administration of epinephrine is associated with favorable outcomes for infants and children in cardiac arrest.
- Rapid defibrillation remains the priority for cardiac arrest with initial shockable rhythms. Administer epinephrine if defibrillation is not immediately possible.
- Assess for treatable causes early. Hypoxemia particularly remains a common cause of cardiac arrest in pediatrics.
- End-tidal carbon dioxide (ETCO2) can be an indicator of CPR quality. The use of specific ETCO2 cutoff values to guide termination of resuscitation in infants and children is not advised.
- Preventing hyperthermia is a critical component of post–cardiac arrest care. Avoiding central temperatures >37.5 °C can improve neurological outcomes in infants and children who remain comatose following cardiac arrest.
- Avoid hypotension in post-cardiac arrest care. New data supports maintaining systolic and mean arterial blood pressure greater than the 10th percentile for age and sex.
- Scene time should allow for establishing critical interventions prior to transport. A scene time between 10 to 35 minutes is associated with best outcomes for pediatric out-of-hospital cardiac arrest.
Referral Information
All pediatric cardiac arrest patients with ROSC require emergency conveyance to hospital.
Pediatric patients with a prolonged pulseless condition and futile cases should be discussed with CliniCall.
General Information
-
- Bystander CPR, plus early defibrillation, can more than double the rate of survival from out-of-hospital cardiac arrest.
- Although survival from asystole or pulseless electrical activity is rare, patients who receive immediate, high-quality CPR can survive.
- Asystole in cardiac arrest is usually an ominous prognostic sign indicating prolonged hypoperfusion and myocardial ischemia with deterioration to asystole from more treatable dysrhythmias.
- Pulseless electrical activity (PEA) is evidence of organized electrical activity on the ECG without effective myocardial contraction.
- Hypothermia-induced cardiac arrest patients should receive prolonged resuscitation, external and internal rewarming, and transport to a facility capable of providing ECMO when feasible. Include CliniCall early in cases of hypothermia-induced cardiac arrest to support decision-making.
- Treatable causes include:
- H’s: Hypovolemia, hypoxemia, acidosis (hydrogen ion), hypo/hyperkalemia, hypothermia, hypoglycemia
- T’s: Tension pneumothorax, tamponade (cardiac), toxins, thrombosis (coronary), thrombosis (pulmonary)
Interventions
First Responder (FR) Interventions
- Compression to ventilation ratio of 15:2, compression rate of 100-120 per minute, and 1/3rd the depth of chest allowing full recoil.
- → PR06: High Performance CPR (Current Guideline)
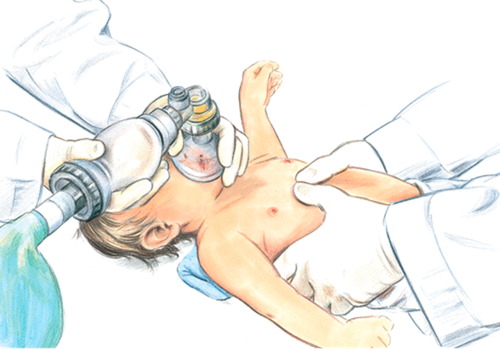
- Airway management and frequent reassessment.
- B01: Airway Management
- A07: Oxygen Administration
- Defibrillation (AED). Apply and follow prompts, minimizing interruption of CPR.
Emergency Medical Responder (EMR) & All License Levels Interventions
Warning: pediatric pads must be used when managing cardiac arrest in children under the age of 8.
Use of adult aed/therapy pads in children under the age of 8 can result in electrical arcing, severe patient burns, and a significant fire hazard.
-
- R: Resuscitation Decision-Making
- CliniCall consultation is required, when possible, to discuss treatment plan and conveyance.
- For penetrating trauma or high-mechanism blunt trauma:
Primary Care Paramedic (PCP) Interventions
Warning: pediatric pads must be used when managing cardiac arrest in children under the age of 8.
Use of adult aed/therapy pads in children under the age of 8 can result in electrical arcing, severe burns, and a significant fire hazard.
- Supraglottic airway devices may be used to maintain airway patency as necessary.
- Obtain vascular access if treatable causes are identified.
- D03: Vascular Access (in patients ≥ 12 years of age)
- PR12: Intraosseous Cannulation (in patients ≥ 12 years of age)
Advanced Care Paramedic (ACP) Interventions
- Manual rhythm interpretation and defibrillation.
- Initial defibrillation dose: 2 J/kg
- Subsequent defibrillation doses: 4 J/kg
- Obtain vascular access.
- D03: Vascular Access
- PR12: Intraosseous Cannulation
- EPINEPHrine
- Ventricular fibrillation/Ventricular Tachycardia:
- Torsade de Pointes:
- Hypovolemia:
- Normal saline 20 ml/kg IV/IO
- Hypoglycemia:
- Tension Pneumothorax
- Toxicological / Antidote
- Hydrogen ion (preexisting acidosis):
- Sodium bicarbonate May be harmful when used routinely
- Hyperkalemia:
- Calcium Chloride May be harmful when used routinely
- Sodium bicarbonate May be harmful when used routinely
- E03: Hyperkalemia
Critical Care Paramedic (CCP) Interventions
Ultrasonography:
-
- Rule out tamponade
- Rule out tension pneumothorax
Consider blood products in massive hemorrhage causing cardiac arrest.
Algorithm
References
- American Heart Association. AHA Guidelines for Cardiopulmonary Resuscitation and Emergency Cardiovascular Care. 2025. [LINK]
- Resuscitation Journal. Time on the scene and interventions are associated with improved survival in pediatric out-of-hospital cardiac arrest (Tjissen, 2015). [LINK]
- UpToDate. Pediatric Advanced Life Support (PALS). [LINK]